

As much as I believe in the healing powers of music, a better understanding of the convoluted American health care system can sure help, too. These days, proper recovery time often takes a backseat to profit. Wikipedia agrees when defining convalescence: “Traditionally time has been allowed for convalescence to happen. Nowadays, in some instances, where there is a shortage of hospital beds or of trained staff, medical settings can feel rushed and may have drifted away from a focus on convalescence.”
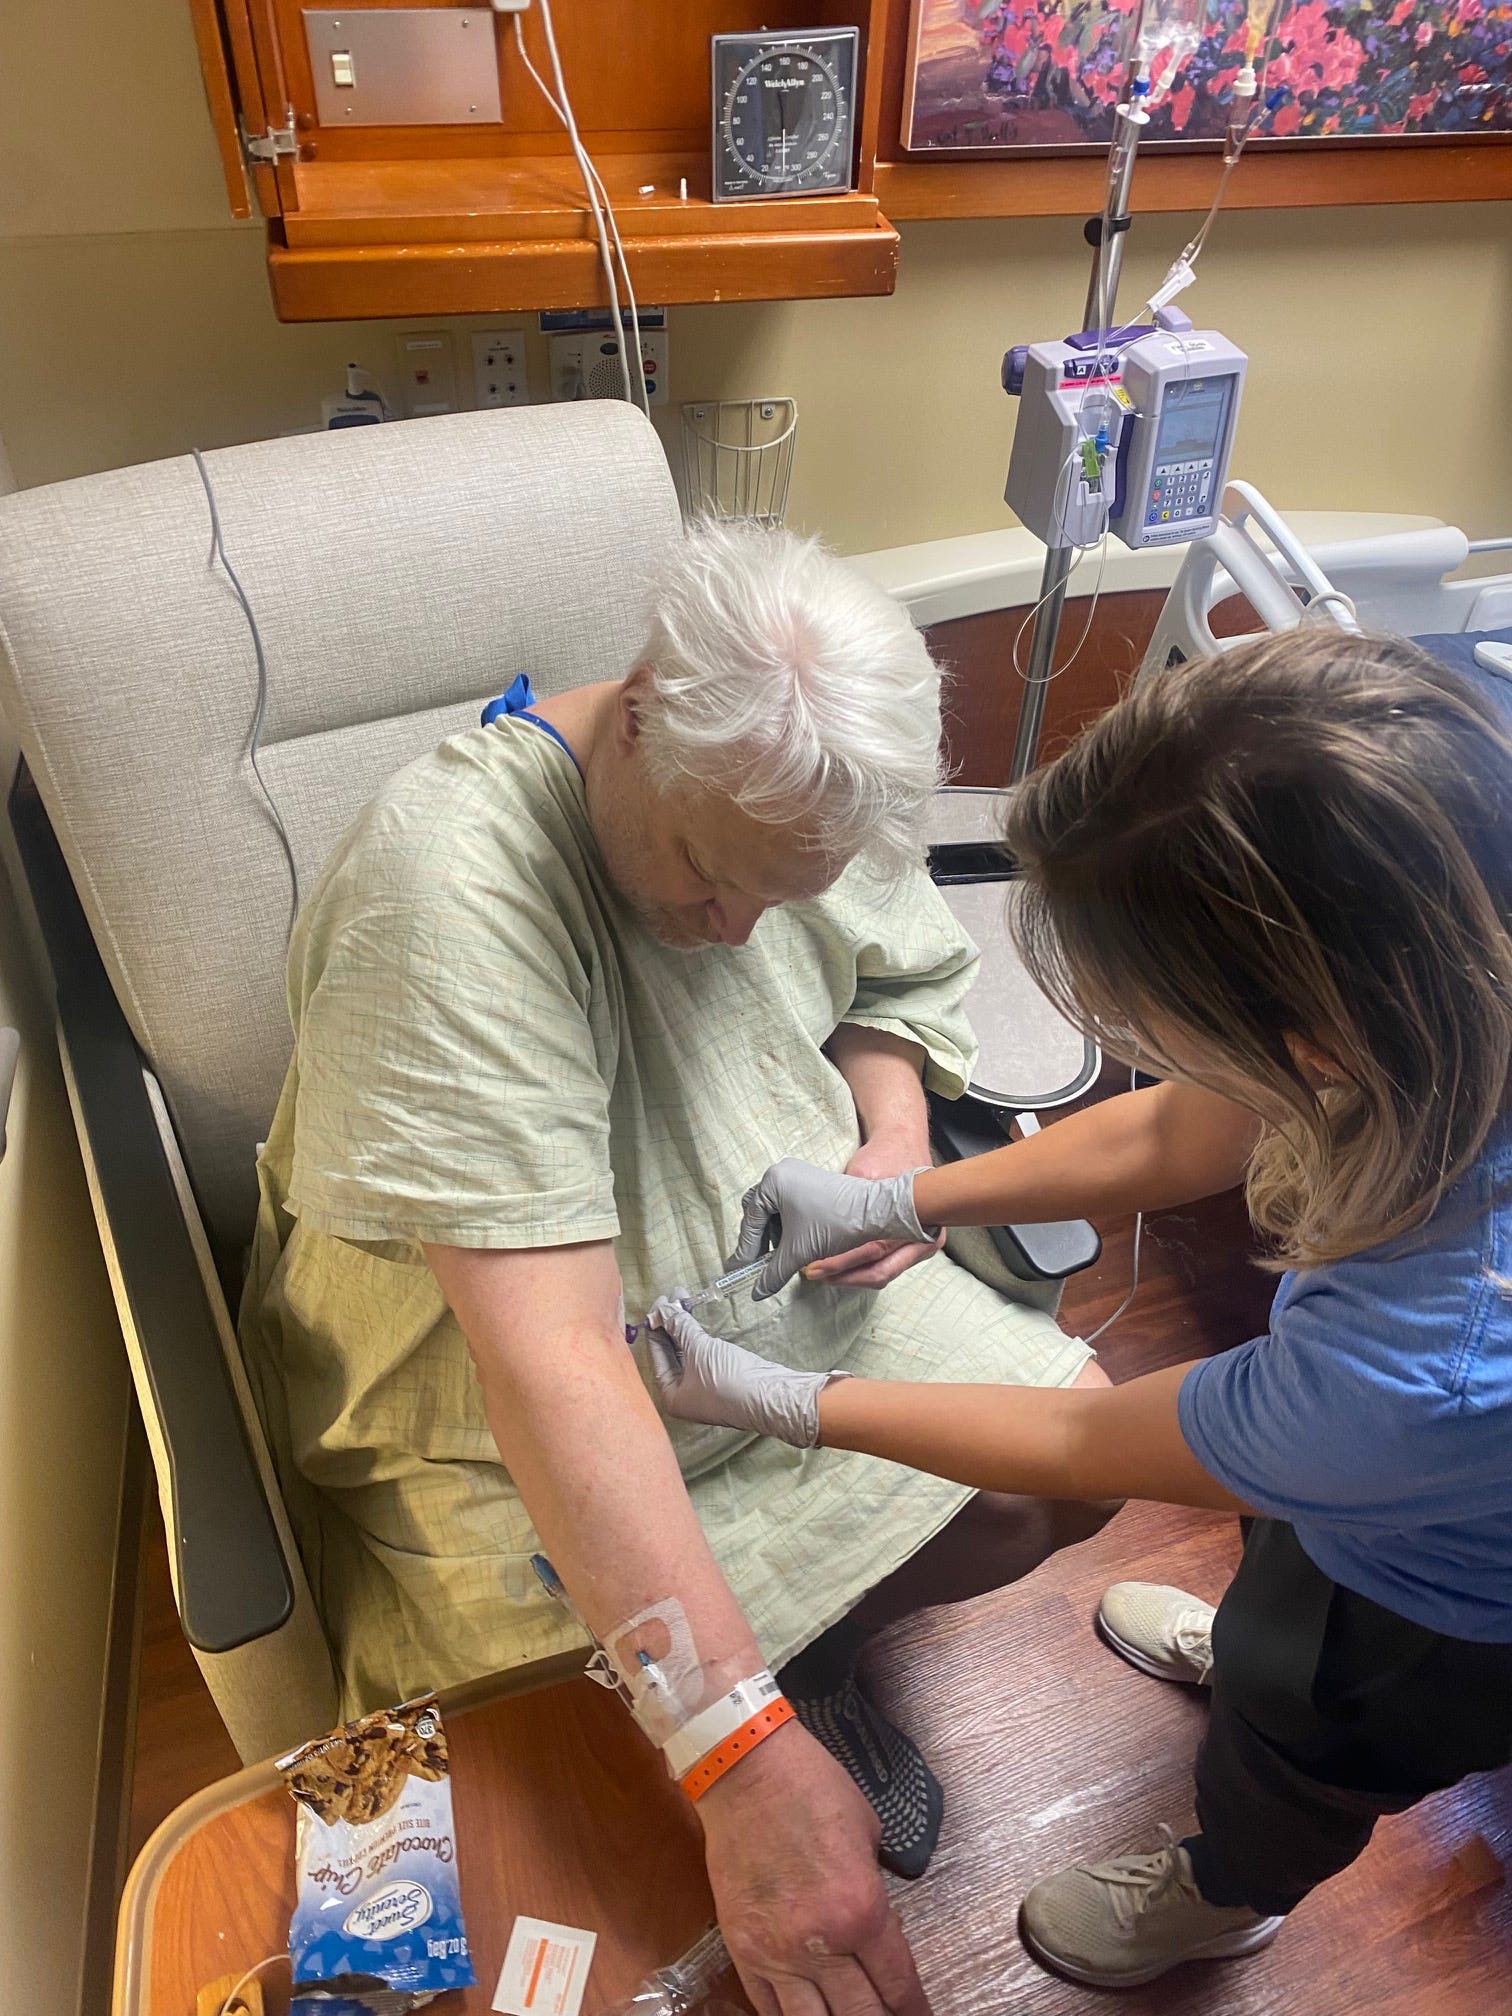
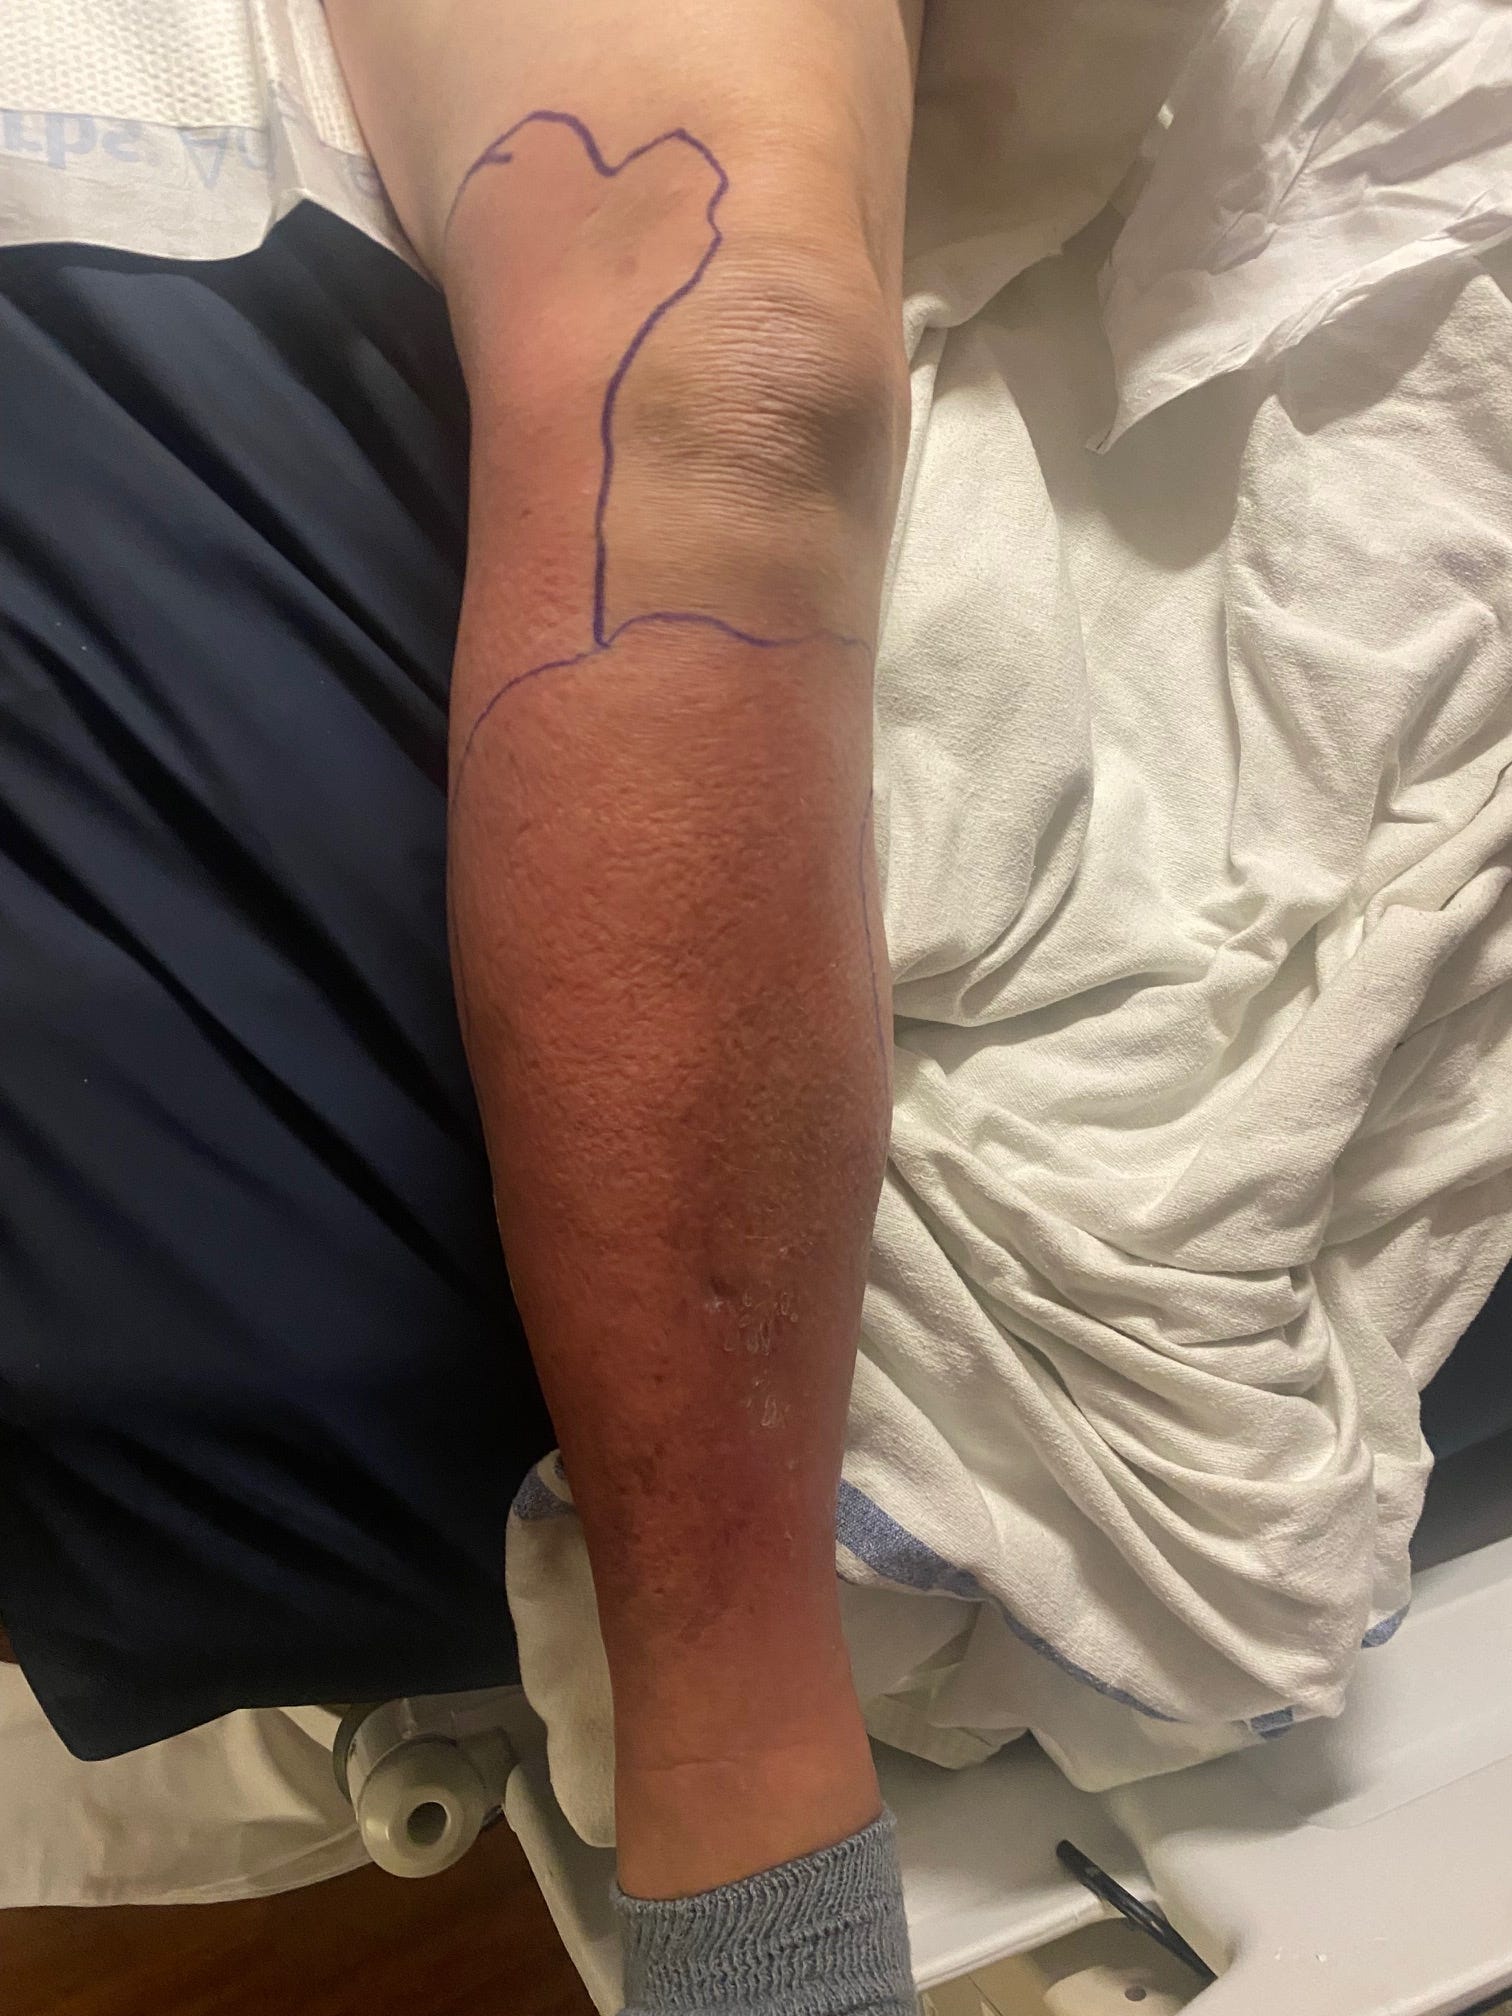
Back in late August, my wife’s 69-year-old uncle, Pete Sorensen, was suddenly knocked down by sepsis. The infection hit him like a ton of bricks, and he landed in the emergency room with severe delirium and excruciating pain. His right leg reddened and ballooned; he was “weak as a kitten,” unable to walk. Pete spent two weeks in Methodist West Hospital in West Des Moines, IA, as doctors and staff worked to battle back the stubborn infection.
After a couple of weeks, the care team decided to move Pete out of the hospital and into the next phase of his recovery. He still needed quite a bit of help—walking was still a challenge, and he required daily IV antibiotics, physical therapy, and other additional care and instruction. His choices for continued convalescence were between a skilled nursing facility (that his Medicare Advantage plan would likely cover) or home health care. Because he has a supplemental home health care policy that will pay him directly for receiving care, the choice was simple. He just needed a soft landing with in-home caregivers to assist in some day-to-day living activities, so my wife and I offered up our guest room for this next period of recuperation. We love Uncle Pete and he was beyond ready to transition from the hospital to a “real bed.”

Pete’s care team was thrilled that he had a solid plan in place, as continued quality of care after leaving the hospital can be an issue for many patients. He still needed daily IV infusions and couldn’t perform two of the ADLs (Activities of Daily Living: bathing, continence, dressing, eating, toileting and transferring) unassisted, so having us around to help out greatly improved the odds of his continued healing.
Home health care is increasingly a more cost-effective solution for insurance companies, and it’s often preferred by all involved if a patient can receive the assistance they need on the homefront. During the COVID-19 pandemic, the health care system found many efficiencies with the home health care approach. Additionally, most patients prefer recovering in the comfort of their own home when possible.
In the last five years, more than 40 million Americans have functioned as caregivers. Many of these caregiver journeys are arduous and more than 80% of caregivers do not receive any respite care, often meaning their own health declines, both physically and mentally. Caregiver stress is all too real in America these days.

Uncle Pete’s policy is tied to a program that not only supports the patient receiving help at home, but it connects the primary caregiver with a plan of action through TCARE. (My wife was assigned as the primary caregiver as she was also assisting him with the central line infusions.) The Caregiver Specialist from TCARE helps caregivers navigate all sorts of new landscapes, from recognizing burnout to reducing workload. After an initial assessment, a check for $3500 is issued to support the caregiver—this is independent of the payments to the patient.
This was our third extended caregiving experience, but the first time we had a policy to provide this level of additional support. Of course, caring for someone in a short-term, acute recovery situation is much different than many of the issues that come with dementia and end-of-life care. We lost my wife’s parents to cancer and dementia, so we have real world experience on this front, as well.

Helping Uncle Pete get back on his feet is something we feel good about. It’s nice to be there for family when you can. We no doubt benefited from our previous experiences and from him being on a supplemental health insurance policy that covered all of our out-of-pocket caregiver expenses in both time and provisions. The supplemental policy is even going to get him the money to cover his out-of-pocket costs from his Medicare Advantage plan through United Healthcare that was $475/day in the hospital days 1 through 6.
In full transparency, I was the insurance agent that wrote the policy and recommended it to Uncle Pete earlier this year. When I learned about the nuances of a short-term home health care policy about a year ago, I couldn’t take my mind off of how much it would have helped us in the past and that others would likely benefit from the policy as well. Reimbursement and the encouragement for home health aide visits alone is a gamechanger because bathing a family member can be a real source of stress and the professionals are so much better at it, so why not get that scheduled with a home health aide? We knew that given his bachelor status and the lack of other family members nearby and capable of assisting, we would most likely be in the position to help out if he needed us.

Uncle Pete was a gracious patient, and the process was pretty smooth overall, especially once the infection finally started to retreat. We welcomed consistent visitors with extensive medical training—physical therapists, occupational therapists, home health aides and registered nurses—into our home. After three weeks of home health care, he was ready to be discharged and set free to roam this beautiful earth once again with a near-death experience officially in his rear-view mirror. There was certainly new pep in his step.
If you or someone you know are interested in learning the nuances of this policy, please feel free to contact me here. The policy is available for people between the ages of 55 and 85. It also comes with a prescription drug benefit making it more affordable for folks. It doesn’t have an elimination period (which many long-term care policies do often starting at 90 days) nor does it require a hospital stay to utilize. The patient just needs to be certified by a healthcare practitioner for cognitive impairment or the inability to perform two of the 6 ADLs without assistance. It’s an alternative approach to long-term care insurance and has quite a bit of utility in today’s health care environment. Pete’s policy will even fully restore after 6 months of wellness.
I am licensed in Iowa, Kansas and Missouri. Consulting with folks about health insurance is an important element to our economic survival now as a writer and musician. Seemingly an odd combination, but with my personal experience as a caregiver and learning that the origins of the Grand Old Opry were originally funded by an insurance campaign, it’s been a career choice I’m pleased to have made. Helping others heal and better navigate stressful times feels pretty good and it’s allowing me to maintain my independence. If we someday move to a single payer health care system, I’ll happily find another way to subsidize this life. Until then, please visit www.chiphappens.life to learn more and please holler if you have any questions.

NOTE: All annual paid subscribers to Chip Happens will now receive a copy of my 2025 CD compilation, Twenty-Five, that includes 25 original songs. To those of you that have already upgraded and purchased the CD, my sincerest of thanks! You are a critical component of making Chip Happens! You can upgrade your subscription here and receive a copy for your physical music collection. If you are only in the market for the CD, it is available here for $25. CD art and design were completed by my amazing and talented wife, Jen Albright.
You all such wonderful care givers!